Scaphoid
Also called scaphoid bone, navicular bone of the hand
A boat-shaped wrist bone on the thumb side that links the two rows of wrist bones. Where it sits, how blood reaches it, who breaks it and how, and how long its parts take to join again.
- Region
- Wrist & hand
- Updated
- October 14, 2026
- Reviewed
- October 14, 2026 · how entries are checked
Function
Where it sits
The carpal bones lie in two rows, one next to the forearm and one next to the palm1. An anatomy textbook lists the scaphoid as the first bone on the thumb side of the forearm row1. The 1918 edition of Gray’s Anatomy calls it the largest bone of that row6. Its name means boat-shaped1.
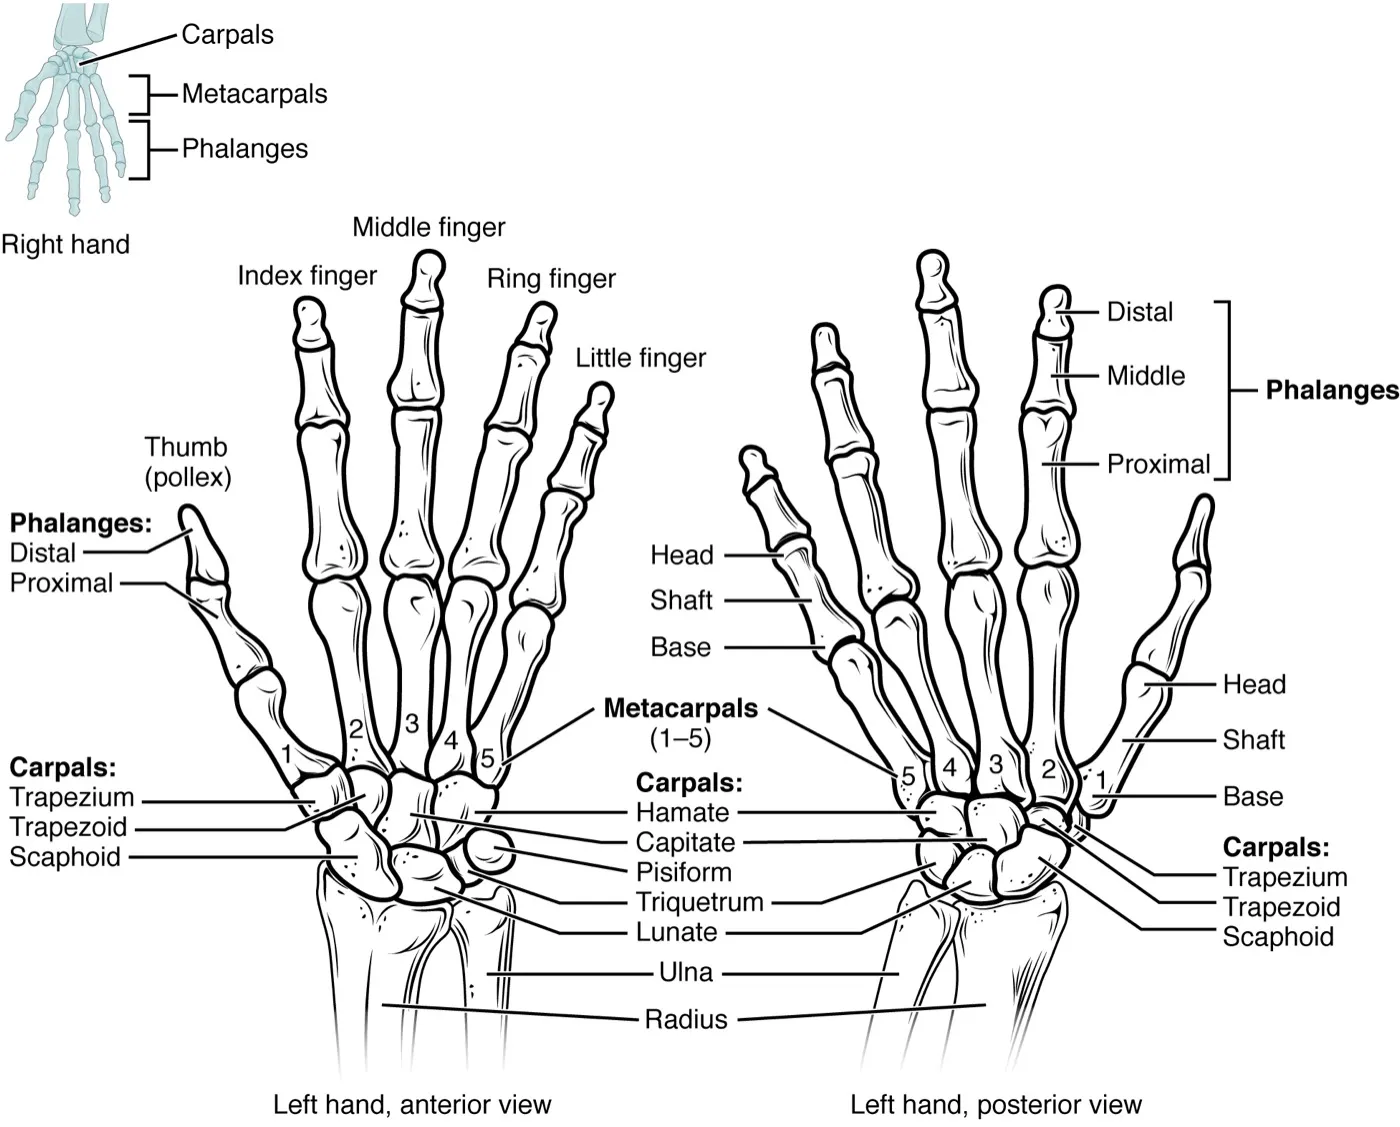
Its surfaces and neighbours
In Gray’s 1918 description the scaphoid meets five bones6:
- the radius (the forearm bone on the thumb side), on its forearm side6;
- the trapezium and trapezoid, two carpal bones of the palm row, on its hand side1,6;
- the capitate and lunate, two more carpal bones, on its inner side1,6.
A 2020 review states that cartilage covers about 80% of the bone’s surface, where it meets those neighbours4. Cartilage is a firm, rubbery body tissue, softer than bone.
Gray describes two landmarks. The palm-side surface rises at its lower, outer part into a rounded bump, the tubercle6. The back (dorsal) surface carries a narrow, rough groove along the whole length of the bone, where ligaments attach6.
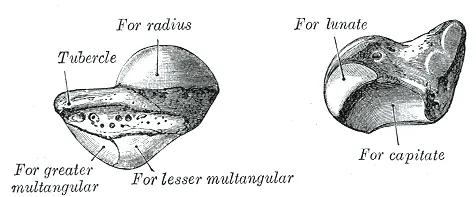
Its parts
Studies divide the bone along its length in two ways. Some name a proximal third, a waist and a distal third4. Others name proximal, middle and distal thirds8. Distal means farther from the centre of the body.
In a scan study of 43 hand specimens, the centre of the waist lay in the middle part of the bone9. Its exact place varied between specimens, and the authors describe the waist as narrow9.
Sources do not agree on where the proximal end begins4,10,11:
- A 2022 review of 12 articles found three main terms: “proximal” in one, “proximal third” in three and “proximal pole” in eight11. Only six gave a specific anatomical or ratio description11.
- A 2013 meta-analysis and a 2020 review both state that the term lacks a consistent definition4,10. Both name the proximal fifth of the bone as a suggested definition4,10.
- The published plan of the SWIFFT trial describes the proximal pole as the bone’s proximal fifth12.
A link between the two rows
Two reviews describe the scaphoid as a mechanical link between the two rows of wrist bones4,13. A review of wrist biomechanics states that no muscle acting on the wrist attaches to the scaphoid’s row14. The row moves only through the forces of the joints around it14.
In a CT study of both wrists of 10 people, the scaphoid contributed 73% of the capitate’s motion in wrist flexion (bending the wrist forward)15. In wrist extension (bending the wrist back) it contributed 99%15.
How load passes through it
Computer models and a review give the radius–scaphoid joint the largest single share of the load crossing the wrist14,16,17.
| Source and wrist position | Share of load through the radius–scaphoid joint |
|---|---|
| Model from 120 wrist X-rays, light grasp, neutral | 55%16 |
| Review of wrist biomechanics, wrist and forearm neutral | About 45%14 |
| Model from CT scans of 7 normal subjects, neutral | 52%17 |
| The same model of 7 subjects, wrist fully extended | 62%17 |
An anatomy article states that the joint surfaces at the bone’s two ends are offset13. The scaphoid therefore tends to flex toward the palm when loaded along its length13.
How blood reaches it
In an injection study of 15 fresh cadaver specimens, the main supply came from the radial artery2. Branches entering through the dorsal ridge supplied most of the vessels inside the bone and the whole proximal pole2. Palm-side branches supplied 20 to 30% of the bone, around the distal tuberosity2. A 2020 review puts the dorsal vessels’ share at 70 to 80% and calls them the only supply to the proximal pole4.
Two later cadaver studies add detail18,19:
- In a micro-CT study of 13 injected upper limbs, a network entering at the dorsal ridge fed 83% of the bone’s volume on average18.
- A study of 12 uninjured cadaver hands found palm-side, dorsal and radial groups of vessels with a variety of connections between them19. Its authors wrote that these should provide enough collateral flow in some patients19.
An anatomy article states that the nutrient vessels enter distally and blood inside the bone runs backwards13. It says a fracture proximal to the waist is prone to displacement, which predisposes the proximal fragment to too little blood flow13.
Breakdown
Who breaks it
A systematic review of 42 epidemiology studies found that adult scaphoid fractures occur mostly in males, with a peak at ages 20 to 293. Females peaked earlier, at 10 to 19 years3. The review’s authors found the studies differed substantially in populations, criteria and outcome measures, and rated the evidence as low3.
Counts of incidence (how many new cases appear in a group over a set time) come from very different populations20,21. Person-years are a count of people multiplied by the years each was followed.
| Population studied | What was found |
|---|---|
| 211,719 people in Bergen, Norway, over three years | 4.3 per 10,000 people a year; 82% of the fractures in males; mean age 2520 |
| A defined adult population, one year, X-ray-confirmed fractures | 29 per 100,000 a year; 105 of the 151 fractures in males22 |
| Swedish National Patient Register, 2006 to 2015 | 22 true fractures per 100,000 person-years, after a check of 300 records found 41% were false positives23 |
| All four United States military services | 1.21 per 1,000 person-years, unadjusted; highest at ages 20 to 2421 |
How it breaks
A 2020 review describes the typical injury as a fall in sport onto an outstretched hand that bent the wrist back4. In a one-year study of 151 fractures, low-energy falls from standing height were the most common cause, at 40.4%22.
Sources describe the mechanics in different ways13,17,24:
- An anatomy article states that extending the scaphoid puts steadily rising tension on the palm-side surface of its curved waist13.
- In a computer model of 7 normal wrists, force concentrated at the scaphoid with the wrist extended17. Its authors concluded that the analysis showed how a bending force causes scaphoid fracture17.
- The authors of a finite element (computer model) study of 12 wrists wrote that the mechanism of waist fracture is not completely understood24.
Where it breaks
The 2020 review states that waist fractures make up two-thirds of scaphoid fractures4. Fractures of the distal third make up 25%, and 5 to 10% are in the proximal third4.
The same 2020 review states that X-rays detect no more than 70% of scaphoid fractures4. The scaphoid fracture page covers what studies of scans found.
When the bone does not join
Nonunion is a broken bone that fails to join and heal. The systematic review of 42 studies put its risk after an adult scaphoid fracture at between 2% and 5%3. Two meta-analyses report higher figures for groups of fractures managed without surgery10,25. A meta-analysis pools the results of several earlier studies.
- Proximal fractures. In a 2013 meta-analysis, 34% of proximal fractures went on to nonunion, 7.5 times the risk of more distal fractures10.
- Displaced fractures. In a 2012 meta-analysis of seven observational studies, nonunion followed 18% of fractures displaced by at least 1 mm25. That was 4.4 times the risk of undisplaced fractures25.
A 2022 meta-analysis of 15 articles grouped proximal fractures by the term each study used11. Against fractures elsewhere in the bone, nonunion was 2.3 times as likely for “proximal third” fractures and 3.4 times for “proximal pole” ones11.
A 2020 review states that a large lever-arm stress acts on the proximal part of the bone, especially in extension4. Together with a tenuous blood supply, it says, this predisposes proximal pole fractures to slower union and a higher risk of nonunion4.
In 12 men operated on for middle-third fractures, biopsy showed avascular necrosis, in which bone loses its blood supply, in the proximal fragment in six26. A systematic review of 27 studies concluded that there is no standard way to tell it from irreversible bone death27.
Two reviews give very different figures for how often it follows a fracture, each in its background28,29:
- A 2008 review states that it is reported in 13% to 50% of scaphoid fractures, and more often when the proximal fifth is involved28.
- A 2022 systematic review states that about 3% of scaphoid fractures show it in the proximal pole29.
Stress fractures
A stress fracture is a small crack in a bone from repeated loading. A 2016 review states that scaphoid stress fractures are very rare, with only case reports in the peer-reviewed literature30. Gymnasts were the athletes most often affected30. In every reported case the fracture was at the waist30.
Recovery
How it joins again
A 2020 review states that scaphoid fractures unite by direct remodelling of the bone, with no callus forming on the outside4. Callus is new tissue that forms around a broken bone and bridges the break as it heals. The review adds that this kind of healing is hard to see and judge on X-rays4. The bone tissue page covers how bone repairs itself in general.
How long each part takes
One CT study followed 219 patients whose acute fractures were managed in a cast alone, and 95% united5.
| Part of the bone | Time to union |
|---|---|
| Proximal pole | 113 days5 |
| Waist | 65 days5 |
| Distal pole | 53 days5 |
The 2020 review describes the distal third as well supplied with blood4. It states that most distal fractures heal without incident after four to six weeks of immobilisation, depending on the fracture type4.
What went with slower or failed union
- Displacement. In a single-centre study of 502 patients aged 16 or over managed in a cast, 50 fractures (10%) did not unite31. The risk tripled when displacement was 1 mm or more31.
- Shape of the break. In the CT study of 219 patients, nonunion was more likely when fragments had shifted sideways or the bone had bent into a humpback shape5.
Cast or surgery
One trial, SWIFFT, randomly assigned adults with waist fractures at 31 hospitals to early surgical fixation or a below-elbow cast32. The scaphoid fracture page reports what such trials found.
Connections
Joints and bones
At the radiocarpal joint of the wrist, the scaphoid and lunate meet the end of the radius directly1.
Ligaments
In eight cadaver arms moved in a wrist simulator, the scapholunate ligament appeared to be the primary stabiliser between the scaphoid and lunate33. A systematic review of 58 anatomy reports found that only one scaphoid ligament, the scaphocapitate, had been described consistently34.
Exercise
Related exercise pages: push-up and bench press. In eight cadaver wrists, an extended-wrist push-up position caused significantly greater peak pressure in the radius–scaphoid part of the joint than a knuckle position35. One case report describes a 21-year-old male cadet who hurt his wrist doing a bench press36. X-rays confirmed a non-displaced fracture through the middle of the scaphoid waist36.
Scaphoid is part of
Scaphoid meets at the wrist joint
Scaphoid is joined to the lunate by
Scaphoid is the bone broken in
Scaphoid is a rare site of
Scaphoid is made of
Scaphoid is loaded by
Sources
- Betts JG, Young KA, Wise JA, Johnson E, Poe B, Kruse DH, Korol O, Johnson JE, Womble M, DeSaix P (2022). Anatomy and Physiology 2e. OpenStax. Link
- Gelberman RH, Menon J (1980). The vascularity of the scaphoid bone.. The Journal of hand surgery. doi:10.1016/s0363-5023(80)80087-6 PMID 7430591
- Jørgsholm P, Ossowski D, Thomsen N, Björkman A (2020). Epidemiology of scaphoid fractures and non-unions: A systematic review.. Handchirurgie, Mikrochirurgie, plastische Chirurgie. doi:10.1055/a-1250-8190 PMID 32992390
- Clementson M, Björkman A, Thomsen NOB (2020). Acute scaphoid fractures: guidelines for diagnosis and treatment.. EFORT open reviews. doi:10.1302/2058-5241.5.190025 PMID 32175096
- Grewal R, Suh N, Macdermid JC (2013). Use of computed tomography to predict union and time to union in acute scaphoid fractures treated nonoperatively.. The Journal of hand surgery. doi:10.1016/j.jhsa.2013.01.032 PMID 23531510
- Gray H; Lewis WH (editor) (1918). Anatomy of the Human Body. Lea & Febiger, Philadelphia (20th edition). Link
- Agrawal A (2019). Musculoskeletal etymology: What's in a name?. Journal of clinical orthopaedics and trauma. doi:10.1016/j.jcot.2018.02.009 PMID 30828213
- Yildiran G, Koplay TG, Akdeniz H, Tosun Z, Karabulut AK (2025). Bone Mineral Density in the Scaphoid.. Plastic surgery (Oakville, Ont.). doi:10.1177/22925503241292351 PMID 39569071
- Ahrend MD, Teunis T, Noser H, Schmidutz F, Richards G, Gueorguiev B, Kamer L (2021). 3D computational anatomy of the scaphoid and its waist for use in fracture treatment.. Journal of orthopaedic surgery and research. doi:10.1186/s13018-021-02330-8 PMID 33761965
- Eastley N, Singh H, Dias JJ, Taub N (2013). Union rates after proximal scaphoid fractures; meta-analyses and review of available evidence.. The Journal of hand surgery, European volume. doi:10.1177/1753193412451424 PMID 22736744
- Chong HH, Kulkarni K, Shah R, Hau MYT, Athanatos L, Singh HP (2022). A meta-analysis of union rate after proximal scaphoid fractures: terminology matters.. Journal of plastic surgery and hand surgery. doi:10.1080/2000656X.2021.1979016 PMID 34550858
- Dias J, Brealey S, Choudhary S, Cook L, Costa M, Fairhurst C, Hewitt C, Hodgson S, Jefferson L, Jeyapalan K, Keding A, Leighton P, Rangan A, Richardson G, Rothery C, Taub N, Thompson J, Torgerson D (2016). Scaphoid Waist Internal Fixation for Fractures Trial (SWIFFT) protocol: a pragmatic multi-centre randomised controlled trial of cast treatment versus surgical fixation for the treatment of bi-cortical, minimally displaced fractures of the scaphoid waist in adults.. BMC musculoskeletal disorders. doi:10.1186/s12891-016-1107-7 PMID 27260639
- Berger RA (2001). The anatomy of the scaphoid.. Hand clinics. PMID 11775465
- Eschweiler J, Li J, Quack V, Rath B, Baroncini A, Hildebrand F, Migliorini F (2022). Anatomy, Biomechanics, and Loads of the Wrist Joint.. Life (Basel, Switzerland). doi:10.3390/life12020188 PMID 35207475
- Wolfe SW, Neu C, Crisco JJ (2000). In vivo scaphoid, lunate, and capitate kinematics in flexion and in extension.. The Journal of hand surgery. doi:10.1053/jhsu.2000.9423 PMID 11040301
- Schuind F, Cooney WP, Linscheid RL, An KN, Chao EY (1995). Force and pressure transmission through the normal wrist. A theoretical two-dimensional study in the posteroanterior plane.. Journal of biomechanics. doi:10.1016/0021-9290(94)00093-j PMID 7775494
- Majima M, Horii E, Matsuki H, Hirata H, Genda E (2008). Load transmission through the wrist in the extended position.. The Journal of hand surgery. doi:10.1016/j.jhsa.2007.10.018 PMID 18294538
- Morsy M, Sabbagh MD, van Alphen NA, Laungani AT, Kadar A, Moran SL (2019). The Vascular Anatomy of the Scaphoid: New Discoveries Using Micro-Computed Tomography Imaging.. The Journal of hand surgery. doi:10.1016/j.jhsa.2019.08.001 PMID 31543293
- Oehmke MJ, Podranski T, Klaus R, Knolle E, Weindel S, Rein S, Oehmke HJ (2009). The blood supply of the scaphoid bone.. The Journal of hand surgery, European volume. doi:10.1177/1753193408100117 PMID 19282403
- Hove LM (1999). Epidemiology of scaphoid fractures in Bergen, Norway.. Scandinavian journal of plastic and reconstructive surgery and hand surgery. doi:10.1080/02844319950159145 PMID 10614752
- Wolf JM, Dawson L, Mountcastle SB, Owens BD (2009). The incidence of scaphoid fracture in a military population.. Injury. doi:10.1016/j.injury.2009.03.045 PMID 19535051
- Duckworth AD, Jenkins PJ, Aitken SA, Clement ND, Court-Brown CM, McQueen MM (2012). Scaphoid fracture epidemiology.. The journal of trauma and acute care surgery. doi:10.1097/ta.0b013e31822458e8 PMID 22439232
- Swärd EM, Schriever TU, Franko MA, Björkman AC, Wilcke MK (2019). The epidemiology of scaphoid fractures in Sweden: a nationwide registry study.. The Journal of hand surgery, European volume. doi:10.1177/1753193419849767 PMID 31106681
- Santoshi JA, Behera P, Dwivedi RK, Srivastav A (2023). Mechanism of scaphoid waist fracture: finite element analysis.. The Journal of hand surgery, European volume. doi:10.1177/17531934221145516 PMID 36562119
- Singh HP, Taub N, Dias JJ (2012). Management of displaced fractures of the waist of the scaphoid: meta-analyses of comparative studies.. Injury. doi:10.1016/j.injury.2012.02.012 PMID 22424701
- Trumble TE (1990). Avascular necrosis after scaphoid fracture: a correlation of magnetic resonance imaging and histology.. The Journal of hand surgery. doi:10.1016/s0363-5023(09)90015-6 PMID 2380517
- Jacobi S, Davidovic-Katz E, Moll S, Barrera J, Shah A, Hacquebord JH (2026). Current diagnostic methods for detecting avascular necrosis and irreversible bone death of the proximal pole of the scaphoid: a systematic review.. The Journal of hand surgery, European volume. doi:10.1177/17531934261449042 PMID 42170849
- Kawamura K, Chung KC (2008). Treatment of scaphoid fractures and nonunions.. The Journal of hand surgery. doi:10.1016/j.jhsa.2008.04.026 PMID 18656779
- Testa G, Lucenti L, D'Amato S, Sorrentino M, Cosentino P, Vescio A, Pavone V (2022). Comparison between Vascular and Non-Vascular Bone Grafting in Scaphoid Nonunion: A Systematic Review.. Journal of clinical medicine. doi:10.3390/jcm11123402 PMID 35743472
- Kohring JM, Curtiss HM, Tyser AR (2016). A Scaphoid Stress Fracture in a Female Collegiate-Level Shot-Putter and Review of the Literature.. Case reports in orthopedics. doi:10.1155/2016/8098657 PMID 27563477
- Dean BJF, Saedi F, Riley ND, Ather S, Tsegaye B, Dhiman P, Little C, Sheehan W, Costa ML (2026). Risk factors for scaphoid nonunion in acute fractures treated with cast immobilization.. Bone & joint open. doi:10.1302/2633-1462.78.BJO-2026-0012.R1 PMID 42547050
- Dias JJ, Brealey SD, Fairhurst C, Amirfeyz R, Bhowal B, Blewitt N, Brewster M, Brown D, Choudhary S, Coapes C, Cook L, Costa M, Davis T, Di Mascio L, Giddins G, Hedley H, Hewitt C, Hinde S, Hobby J, Hodgson S, Jefferson L, Jeyapalan K, Johnston P, Jones J, Keding A, Leighton P, Logan A, Mason W, McAndrew A, McNab I, Muir L, Nicholl J, Northgraves M, Palmer J, Poulter R, Rahimtoola Z, Rangan A, Richards S, Richardson G, Stuart P, Taub N, Tavakkolizadeh A, Tew G, Thompson J, Torgerson D, Warwick D (2020). Surgery versus cast immobilisation for adults with a bicortical fracture of the scaphoid waist (SWIFFT): a pragmatic, multicentre, open-label, randomised superiority trial.. Lancet (London, England). doi:10.1016/S0140-6736(20)30931-4 PMID 32771106
- Short WH, Werner FW, Green JK, Masaoka S (2002). Biomechanical evaluation of ligamentous stabilizers of the scaphoid and lunate.. The Journal of hand surgery. doi:10.1053/jhsu.2002.35878 PMID 12457349
- Buijze GA, Lozano-Calderon SA, Strackee SD, Blankevoort L, Jupiter JB (2011). Osseous and ligamentous scaphoid anatomy: Part I. A systematic literature review highlighting controversies.. The Journal of hand surgery. doi:10.1016/j.jhsa.2011.09.012 PMID 22051230
- Daly BT, Werner FW, Cavallaro SM, Tucci ER, Harley BJ (2018). Effect of Push-Up Position on Wrist Joint Pressures in the Intact Wrist and Following Scapholunate Interosseous Ligament Sectioning.. The Journal of hand surgery. doi:10.1016/j.jhsa.2017.10.019 PMID 29157783
- Mason JS, Crowell MS, Goss DL (2015). Fracture of the Scaphoid During a Bench-Press Exercise.. The Journal of orthopaedic and sports physical therapy. doi:10.2519/jospt.2015.0408 PMID 26232322
Changes
- First published.