Scaphoid fracture
Also called scaphoid fractures, broken scaphoid, scaphoid waist fracture, scaphoid nonunion
A break of the scaphoid, a wrist bone on the thumb side. Where it breaks, who breaks it, what follows when it does not join, and what trials of surgery against a cast and studies of return to sport found.
- Region
- Wrist & hand
- Updated
- October 14, 2026
- Reviewed
- October 14, 2026 · how entries are checked
What it is
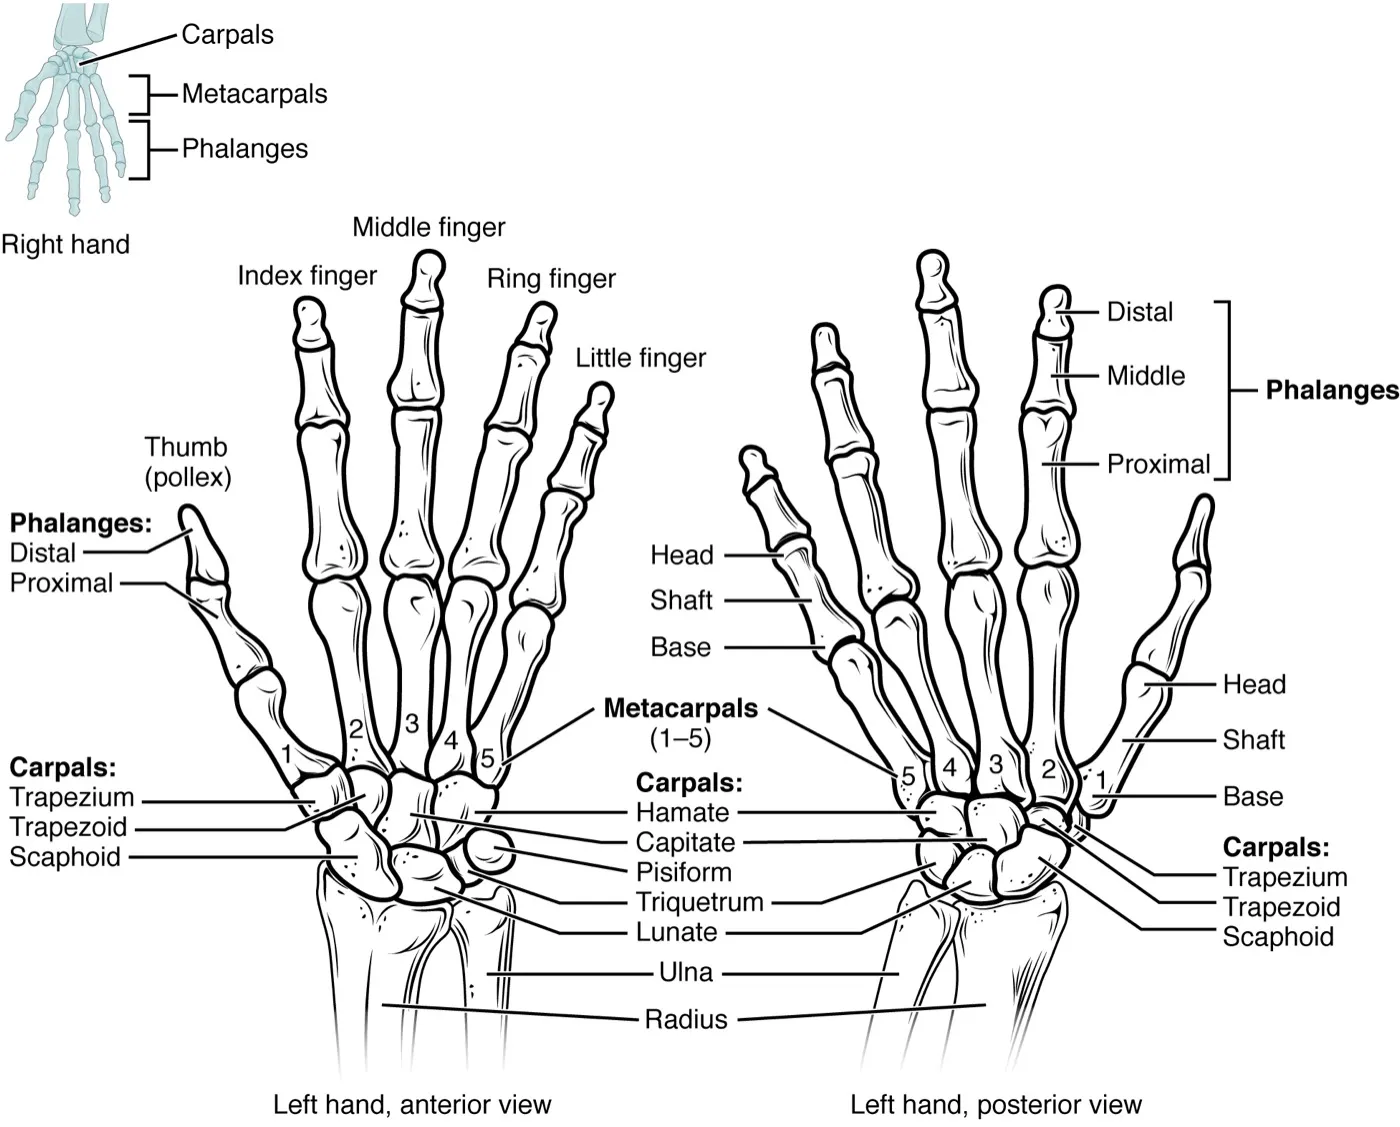
An open anatomy textbook defines a fracture simply as a broken bone1. The same textbook lists the scaphoid as the first carpal bone on the thumb side of the row next to the forearm1. The scaphoid page covers the bone itself, including its blood supply.
How studies define the break
The protocol of SWIFFT, a trial described below, required a break that plain X-rays showed clearly7. The break also had to cross both outer walls of the bone’s waist and be shifted 2 mm or less7. A 2026 systematic review looked at 58 studies of suspected scaphoid fractures8. Nearly half gave no definition of a fracture on MRI, a magnetic scan, and its authors called for an agreed one8.
Where the bone breaks
Proximal means nearer the centre of the body, and distal means farther from it. In scans of 43 hand specimens, the centre of the waist lay in the mid-portion of the bone, and the authors called the waist narrow9. A 2020 review states that fractures of the proximal pole, the end nearer the body, lack a common definition2. Since breaks nearer that end are less likely to join, it notes a proposal to use the bone’s proximal fifth2. The SWIFFT protocol describes the proximal pole the same way7.
The 2020 review states that fractures of the waist make up two-thirds of scaphoid fractures2. Most of those, 60 to 85%, are not displaced2. In a displaced fracture, the bone ends have moved out of line. The review puts 25% in the distal third and 5 to 10% in the proximal third2.
Fractures that first X-rays do not show
The 2020 review states that X-rays detect no more than 70% of scaphoid fractures2. Studies have counted fractures in wrists whose first X-rays looked normal10,11.
| Group studied | Share with a scaphoid fracture |
|---|---|
| 1,685 wrist injuries with normal first X-rays, in a systematic review of eight studies | 9.0%10 |
| 1,989 patients at eight UK centres who had an early MRI scan for a suspected fracture | 12.9% (256 patients)11 |
The 2020 review puts the share at 4 to 20%2.
Who it affects
A systematic review of 42 epidemiology studies found that adult scaphoid fractures occur mostly in males, with a peak at ages 20 to 2912. Females peaked earlier, at ages 10 to 1912. Its authors rated the evidence on who breaks the bone as low12.
The 2020 review describes the typical injury as a fall in sport onto an outstretched hand that bent the wrist back2. An anatomy textbook says the force of such a fall travels up the limb1. It may break the humerus (upper arm bone), the radius (the forearm bone on the thumb side) or the scaphoid1. The distal radius fracture page covers the break at the wrist end of the radius.
A stress fracture is a small crack in a bone from repeated loading. A case report is a report on a single patient. A 2016 case report, which also reviewed the literature, states that scaphoid stress fractures are very rare13. It adds that the peer-reviewed literature holds only case reports of them13.
What studies found
How often the bone fails to join
A 2020 review gives a figure for waist fractures that are not displaced, or displaced by 0.5 mm or less2. After adequate management without surgery, about 90% have united at six weeks2. Counts of nonunion differ with the source and the group counted12,14:
- The systematic review of 42 studies: a risk of 2% to 5% in adults12.
- Swiss accident insurance records, 16,691 fractures: about 14% went on to nonunion, and 3% developed arthritis after the injury14.
- Eight UK centres, 250 fractures found on MRI and managed in a cast: 16 (6.3%) went on to delayed union or nonunion11. Delayed union is a broken bone healing more slowly than expected.
What follows a nonunion over the years
Several studies looked at wrists with a nonunion years after the injury4,15,16,17,18.
| Who was studied | What was found |
|---|---|
| 55 patients with 56 nonunions and no earlier care for them | Arthritis in 31 of the 32 injured five or more years before15 |
| 102 symptomatic patients with 104 nonunions at least a year old | Osteoarthritis in 22% of nonunions under 5 years old, 75% at 5 to 9 years, and 100% at 10 years or more4 |
| 33 patients with a nonunion found on X-ray 2 to 37 years after the injury | Progressive osteoarthritis between the radius and the wrist bones in all 33, at re-examination 10 to 17 years later16 |
| 278 consecutive nonunions imaged a mean of 3.3 years after injury | Osteoarthritis in 62.2%17 |
| 20 people with nonunions of 34 years on average and no intervention | Fair or good function in most, despite reduced movement and grip strength18 |
In the study of 102 patients, pain did not track the severity of arthritis or the age of the nonunion4. Longer duration did go with weaker grip and less wrist motion4.
A 1993 appraisal found that none of the natural history studies of scaphoid nonunion published by then followed patients from the time of injury5. It concluded that the bias in those studies ran toward a worse outcome5. The true course, it said, is less severe than they reported, by an unknown amount5.
Surgery against a cast: the SWIFFT trial
SWIFFT was a randomised trial at 31 hospitals in England and Wales3. It was open-label, so participants and researchers knew who was in which group3. The National Institute for Health Research, through its Health Technology Assessment Programme, funded it3,7. The protocol states that this funder had no part in the study’s design or analysis7. The trial assigned 439 adults with waist fractures shifted 2 mm or less to early surgical fixation or a cast3.
The main measure was the patient-rated wrist evaluation (PRWE), a 15-item questionnaire on wrist pain and function7,22,23. Its total runs from 0, no disability, to 100, and a higher score means worse pain and function7,22,23. At 52 weeks, the adjusted mean scores were 11.9 with surgery and 14.0 with a cast, not a significant difference3.
In the cast group, a fracture was fixed at once if nonunion was confirmed3. The protocol states that two independent radiologists and a surgeon would judge the X-rays and scans7. The same open-label trial, with the same funder, counted complications in each group3,7.
| What the trial counted | Early surgery (219 people) | Cast (220 people) |
|---|---|---|
| A potentially serious complication of surgery | 31 (14%)3 | 3 (1%)3 |
| A cast-related complication | 5 (2%)3 | 40 (18%)3 |
| Nonunion at one year | 124 | 424 |
The trial’s report lists a limitation: 17 participants who began in a cast went on to surgery for confirmed nonunion24. Three of the four in the cast group with a nonunion at 52 weeks were not offered surgery24.
At five years, the wrist score still did not differ significantly between the groups22. Among the 267 of 439 who had imaging at five years, osteoarthritis around the scaphoid was similarly common in both groups23. Three observers read those X-rays and CT scans independently23. The five-year papers name the same funder, and an independent steering committee oversaw the follow-up22,23.
Other trials and pooled reviews
Two other randomised comparisons set screw fixation against a cast25,26. One followed up 71 of its 88 randomised patients at a mean of 93 months25. It found no statistical difference in symptoms and disability, wrist movement, or grip and pinch strength25. The other compared a randomised subgroup with non-displaced waist fractures, 23 in a cast and 15 with a screw26. Time to union did not differ significantly26.
That study assigned groups with a blinded envelope system, and a regional health authority and hospital funded it26. A radiologist and one senior author read all its imaging together, and agreement between readers was not tested26.
Four meta-analyses pooled trials of this one comparison27,28,29,30. A meta-analysis pools the results of several earlier studies to get one combined answer.
| Review | What it found for surgery against a cast |
|---|---|
| 2010, eight randomised trials, 419 patients; fractures not displaced or minimally displaced | Function, measured in four trials, significantly favoured surgery27. No significant difference in nonunion or malunion (a bone that heals out of line)27 |
| 2015, six randomised studies in seven papers, 340 fractures not displaced or minimally displaced28 | Better short-term function and a quicker return to work after surgery28 |
| 2022, seven randomised trials; fractures displaced by 2 mm or less | No significant difference in patient-reported wrist function at 12 months; more complications, and more serious ones, with surgery29 |
| 2023, twelve trials, described as randomised | Shorter healing time and return to work after surgery; no significant difference in nonunion or complications30 |
The 2010 authors wrote that most of the trials lacked scientific rigor27. The 2015 authors wrote that the 2010 review had included one study whose corresponding author confirmed it was not randomised28. The 2015 review counted the 93-month trial above as one study, from its two reports25,28. For displaced fractures, the authors of a 2012 meta-analysis reported no randomised trials of fixation against a cast at that time31.
Return to sport
A 2019 systematic review pooled eleven studies of athletes6. Two were randomised trials, six looked back at past records, and three were case series, with no comparison group6.
| Athletes in the 2019 review | Share who returned to sport | Mean time to return |
|---|---|---|
| Managed without surgery | 90% (69 of 77)6 | 9.6 weeks6 |
| Fixed surgically | 98% (81 of 83)6 | 7.3 weeks6 |
The review’s authors noted that the athletes who went straight back in a cast or splint had a nonunion rate of 15%6. They wrote that this practice skewed the return times for fractures managed without surgery6. They rated their eleven studies’ quality as lower than in similar reviews of other fractures6.
A 2026 systematic review found 10 studies covering 208 scaphoid fractures in athletes32. In it, 135 athletes returned on an early timeline, at a mean of 6.25 weeks32. Another 73, managed without surgery, returned after the fracture had united, at a mean of 13.97 weeks32.
Proximal pole fractures were over-represented among those that ended in nonunion, a repeat break or avascular necrosis32. This was most marked in studies that allowed a very early return in a cast32. The authors wrote that the evidence was mostly case series, small cohorts and case reports32. These designs, they wrote, do not allow a reliable estimate of how often complications occur32.
Connections
The bone, the joint and the ligament
The scaphoid meets the end of the radius directly at the radiocarpal joint of the wrist1. A systematic review of eleven studies looked at injury of the scapholunate ligament alongside an acute scaphoid fracture33. Reported rates ran from 0% to 71% in studies of low to moderate quality, and complete tears were rare33.
Related conditions
In an MRI study of 154 people aged 18 to 49 with a wrist sprain and normal X-rays, 13 had a hidden scaphoid fracture34.
Exercise
Related exercise pages: push-up and bench press. A cadaver is a body donated for study. In eight cadaver wrists, an extended-wrist push-up position caused significantly greater peak pressure at the radius–scaphoid part of the joint than a knuckle position35. One case report describes a 21-year-old male cadet with a non-displaced scaphoid waist fracture after he hurt the wrist doing a bench press36.
Scaphoid fracture involves
Scaphoid fracture has been studied alongside injury of
Scaphoid fracture shares a fall onto the hand with
Scaphoid fracture has been found on scans in people with
Scaphoid fracture is a rare site of
Scaphoid fracture has a lab study of joint pressure during
Scaphoid fracture has one case report during
Sources
- Betts JG, Young KA, Wise JA, Johnson E, Poe B, Kruse DH, Korol O, Johnson JE, Womble M, DeSaix P (2022). Anatomy and Physiology 2e. OpenStax. Link
- Clementson M, Björkman A, Thomsen NOB (2020). Acute scaphoid fractures: guidelines for diagnosis and treatment.. EFORT open reviews. doi:10.1302/2058-5241.5.190025 PMID 32175096
- Dias JJ, Brealey SD, Fairhurst C, Amirfeyz R, Bhowal B, Blewitt N, Brewster M, Brown D, Choudhary S, Coapes C, Cook L, Costa M, Davis T, Di Mascio L, Giddins G, Hedley H, Hewitt C, Hinde S, Hobby J, Hodgson S, Jefferson L, Jeyapalan K, Johnston P, Jones J, Keding A, Leighton P, Logan A, Mason W, McAndrew A, McNab I, Muir L, Nicholl J, Northgraves M, Palmer J, Poulter R, Rahimtoola Z, Rangan A, Richards S, Richardson G, Stuart P, Taub N, Tavakkolizadeh A, Tew G, Thompson J, Torgerson D, Warwick D (2020). Surgery versus cast immobilisation for adults with a bicortical fracture of the scaphoid waist (SWIFFT): a pragmatic, multicentre, open-label, randomised superiority trial.. Lancet (London, England). doi:10.1016/S0140-6736(20)30931-4 PMID 32771106
- Inoue G, Sakuma M (1996). The natural history of scaphoid non-union. Archives of orthopaedic and trauma surgery. doi:10.1007/BF00453208 PMID 8775701
- Kerluke L, McCabe SJ (1993). Nonunion of the scaphoid: a critical analysis of recent natural history studies.. The Journal of hand surgery. doi:10.1016/0363-5023(93)90235-U PMID 8423291
- Goffin JS, Liao Q, Robertson GA (2019). Return to sport following scaphoid fractures: A systematic review and meta-analysis.. World journal of orthopedics. doi:10.5312/wjo.v10.i2.101 PMID 30788227
- Dias J, Brealey S, Choudhary S, Cook L, Costa M, Fairhurst C, Hewitt C, Hodgson S, Jefferson L, Jeyapalan K, Keding A, Leighton P, Rangan A, Richardson G, Rothery C, Taub N, Thompson J, Torgerson D (2016). Scaphoid Waist Internal Fixation for Fractures Trial (SWIFFT) protocol: a pragmatic multi-centre randomised controlled trial of cast treatment versus surgical fixation for the treatment of bi-cortical, minimally displaced fractures of the scaphoid waist in adults.. BMC musculoskeletal disorders. doi:10.1186/s12891-016-1107-7 PMID 27260639
- van Boxel MF, Kaplan A, Ring D, Jaarsma EH, Doornberg JN, Obdeijn MC (2026). Variation in definitions of scaphoid fracture on MRI scans for suspected fracture: a systematic review.. The Journal of hand surgery, European volume. doi:10.1177/17531934251367541 PMID 40844844
- Ahrend MD, Teunis T, Noser H, Schmidutz F, Richards G, Gueorguiev B, Kamer L (2021). 3D computational anatomy of the scaphoid and its waist for use in fracture treatment.. Journal of orthopaedic surgery and research. doi:10.1186/s13018-021-02330-8 PMID 33761965
- Coventry L, Oldrini I, Dean B, Novak A, Duckworth A, Metcalfe D (2023). Which clinical features best predict occult scaphoid fractures? A systematic review of diagnostic test accuracy studies.. Emergency medicine journal : EMJ. doi:10.1136/emermed-2023-213119 PMID 37169546
- Dean BJF, Riley N, Little C, Sheehan W, Gidwani S, Brewster M, Dhiman P, Costa ML (2024). The rate of nonunion in the MRI-detected occult scaphoid fracture.. The bone & joint journal. doi:10.1302/0301-620X.106B4.BJJ-2023-1171.R1 PMID 38555933
- Jørgsholm P, Ossowski D, Thomsen N, Björkman A (2020). Epidemiology of scaphoid fractures and non-unions: A systematic review.. Handchirurgie, Mikrochirurgie, plastische Chirurgie. doi:10.1055/a-1250-8190 PMID 32992390
- Kohring JM, Curtiss HM, Tyser AR (2016). A Scaphoid Stress Fracture in a Female Collegiate-Level Shot-Putter and Review of the Literature.. Case reports in orthopedics. doi:10.1155/2016/8098657 PMID 27563477
- Rothenfluh E, Vögelin E, Scholz SM (2025). The epidemiology of scaphoid fractures and non-unions in Switzerland: a nationwide analysis of the socioeconomic impact.. Scientific reports. doi:10.1038/s41598-025-24729-7 PMID 41258412
- Ruby LK, Stinson J, Belsky MR (1985). The natural history of scaphoid non-union. A review of fifty-five cases.. The Journal of bone and joint surgery. American volume. PMID 3972868
- Lindström G, Nyström A (1992). Natural history of scaphoid non-union, with special reference to "asymptomatic" cases.. Journal of hand surgery (Edinburgh, Scotland). doi:10.1016/0266-7681(92)90204-f PMID 1484258
- Dias JJ, Kheiran A, Ngo DN, Adeleye E, Wildin CJ, Ullah A, Bhowal B, Bindra R (2023). The onset, progress and factors influencing degenerative arthritis of the wrist following scaphoid fracture non-union.. Injury. doi:10.1016/j.injury.2022.12.025 PMID 36621361
- Jerome JTJ (2021). Revisiting the Natural History of Chronic Scaphoid Nonunions: A Retrospective Study of 20 Cases.. Journal of wrist surgery. doi:10.1055/s-0040-1721435 PMID 34631288
- Jacobi S, Davidovic-Katz E, Moll S, Barrera J, Shah A, Hacquebord JH (2026). Current diagnostic methods for detecting avascular necrosis and irreversible bone death of the proximal pole of the scaphoid: a systematic review.. The Journal of hand surgery, European volume. doi:10.1177/17531934261449042 PMID 42170849
- Kawamura K, Chung KC (2008). Treatment of scaphoid fractures and nonunions.. The Journal of hand surgery. doi:10.1016/j.jhsa.2008.04.026 PMID 18656779
- Testa G, Lucenti L, D'Amato S, Sorrentino M, Cosentino P, Vescio A, Pavone V (2022). Comparison between Vascular and Non-Vascular Bone Grafting in Scaphoid Nonunion: A Systematic Review.. Journal of clinical medicine. doi:10.3390/jcm11123402 PMID 35743472
- Dias JJ, Brealey SD, Coleman E, Hicks K, Laycock J, Cook E, Choudhary S, Jeyapalan K, Fairhurst C, Hinde S, Richardson G, Costa ML, Rangan A, Taub N, Torgerson D (2026). Clinical effectiveness of early surgical fixation versus cast immobilization for adults with a scaphoid waist fracture: five-year follow-up of the Scaphoid Waist Internal Fixation for Fractures Trial.. The bone & joint journal. doi:10.1302/0301-620X.108B1.BJJ-2025-0122.R1 PMID 41475372
- Dias JJ, Brealey SD, Coleman E, Choudhary S, Jeyapalan K, Adeleye E, Fairhurst C, Hicks K, Laycock J, Cook E, Costa ML, Rangan A, Hodgson S (2026). Radiological outcome of early surgical fixation versus cast immobilization for adults with a scaphoid waist fracture: five-year follow-up of the Scaphoid Waist Internal Fixation for Fractures Trial.. The bone & joint journal. doi:10.1302/0301-620X.108B1.BJJ-2025-0125.R1 PMID 41475366
- Dias J, Brealey S, Cook L, Fairhurst C, Hinde S, Leighton P, Choudhary S, Costa M, Hewitt C, Hodgson S, Jefferson L, Jeyapalan K, Keding A, Northgraves M, Palmer J, Rangan A, Richardson G, Taub N, Tew G, Thompson J, Torgerson D (2020). Surgical fixation compared with cast immobilisation for adults with a bicortical fracture of the scaphoid waist: the SWIFFT RCT.. Health technology assessment (Winchester, England). doi:10.3310/hta24520 PMID 33109331
- Dias JJ, Dhukaram V, Abhinav A, Bhowal B, Wildin CJ (2008). Clinical and radiological outcome of cast immobilisation versus surgical treatment of acute scaphoid fractures at a mean follow-up of 93 months.. The Journal of bone and joint surgery. British volume. doi:10.1302/0301-620X.90B7.20371 PMID 18591600
- Clementson M, Jørgsholm P, Besjakov J, Björkman A, Thomsen N (2015). Union of Scaphoid Waist Fractures Assessed by CT Scan.. Journal of wrist surgery. doi:10.1055/s-0034-1398472 PMID 25709879
- Buijze GA, Doornberg JN, Ham JS, Ring D, Bhandari M, Poolman RW (2010). Surgical compared with conservative treatment for acute nondisplaced or minimally displaced scaphoid fractures. The Journal of bone and joint surgery. American volume. doi:10.2106/JBJS.I.01214 PMID 20516332
- Shen L, Tang J, Luo C, Xie X, An Z, Zhang C (2015). Comparison of operative and non-operative treatment of acute undisplaced or minimally-displaced scaphoid fractures: a meta-analysis of randomized controlled trials.. PloS one. doi:10.1371/journal.pone.0125247 PMID 25942316
- Johnson NA, Fairhurst C, Brealey SD, Cook E, Stirling E, Costa M, Divall P, Hodgson S, Rangan A, Dias JJ (2022). One-year outcome of surgery compared with immobilization in a cast for adults with an undisplaced or minimally displaced scaphoid fracture : a meta-analysis of randomized controlled trials.. The bone & joint journal. doi:10.1302/0301-620X.104B8.BJJ-2022-0085.R2 PMID 35909381
- Chen S, Zhang C, Jiang B, Mi Y, Zhu Y, Jia X (2023). Comparison of Conservative Treatment and Surgery Treatment for Acute Scaphoid Fracture: A Meta-Analysis of Randomized Controlled Trials.. World journal of surgery. doi:10.1007/s00268-022-06833-1 PMID 36484804
- Singh HP, Taub N, Dias JJ (2012). Management of displaced fractures of the waist of the scaphoid: meta-analyses of comparative studies.. Injury. doi:10.1016/j.injury.2012.02.012 PMID 22424701
- Wang C, Daniels J, Devine D, Simon M, Kirschenbaum D, Katt BM (2026). Evaluating the Safety of Early Return to Play After Metacarpal or Scaphoid Fracture: A Systematic Review.. Cureus. doi:10.7759/cureus.104379 PMID 41913888
- Glévarec L, Njessi P, Poumellec MA, Balaguer T, Camuzard O, Lupon E (2026). Scapholunate Injuries in the Context of Acute Scaphoid Fractures: A Systematic Literature Review.. Hand (New York, N.Y.). doi:10.1177/15589447261430936 PMID 41933503
- Bergh TH, Lindau T, Soldal LA, Bernardshaw SV, Behzadi M, Steen K, Brudvik C (2014). Clinical scaphoid score (CSS) to identify scaphoid fracture with MRI in patients with normal x-ray after a wrist trauma.. Emergency medicine journal : EMJ. doi:10.1136/emermed-2012-202219 PMID 23727599
- Daly BT, Werner FW, Cavallaro SM, Tucci ER, Harley BJ (2018). Effect of Push-Up Position on Wrist Joint Pressures in the Intact Wrist and Following Scapholunate Interosseous Ligament Sectioning.. The Journal of hand surgery. doi:10.1016/j.jhsa.2017.10.019 PMID 29157783
- Mason JS, Crowell MS, Goss DL (2015). Fracture of the Scaphoid During a Bench-Press Exercise.. The Journal of orthopaedic and sports physical therapy. doi:10.2519/jospt.2015.0408 PMID 26232322
Changes
- First published.